
A ventral hernia is a defect in the abdominal wall. An incisional hernia develops at or near the site of a previous surgical incision. These hernias range from small, straightforward defects to complex recurrent hernias involving a large portion of the abdominal wall.
A hernia develops when tissue or intestine pushes through a weakness in the abdominal wall. Prior surgery, obesity, smoking, wound complications, pregnancy, chronic coughing, and other factors can contribute to abdominal wall weakness.
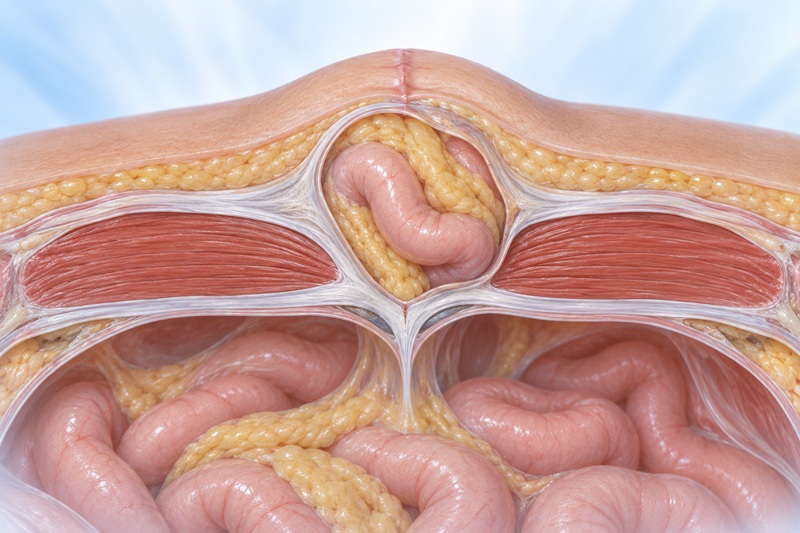
The decision to repair a ventral or incisional hernia depends on symptoms, size, location, growth over time, risk of bowel involvement, prior repairs, and the patient's overall health. Some small asymptomatic hernias can be observed; others are better treated surgically.
Robotic surgery can allow the abdominal wall to be evaluated and reconstructed through small incisions in selected patients. Depending on the hernia, repair may involve closing the defect, restoring the abdominal wall layers, and reinforcing the repair with mesh.
Large, recurrent, or complex hernias may require more than simply covering the defect with mesh. Selected patients may need reconstruction that restores abdominal wall anatomy and function. The operation should be planned around the size and location of the defect, prior mesh, scar tissue, previous surgery, and patient-specific risk factors.
Optimizing modifiable risk factors can improve the safety and durability of hernia repair. Depending on the patient, this may include weight management, smoking cessation, diabetes control, nutritional optimization, and treatment of conditions that increase abdominal pressure.
Potential risks include bleeding, infection, seroma, wound complications, mesh infection or other mesh-related problems, bowel injury, chronic pain, recurrence, blood clots, and anesthesia-related complications. Recurrence risk varies with the hernia, prior repairs, patient factors, and the type of reconstruction required.
Minimally invasive technique with tiny incisions and less soft tissue disruption.
High-definition 3D view allows precise dissection and improved safety.
Mesh is placed to reinforce weak areas and reduce the risk of recurrence.
Less pain and quicker return to daily activities compared to open surgery.
Strong, long-lasting repair designed to restore abdominal wall integrity.
A consultation is needed to determine if robotic repair is right for you.
We review your history and perform a through physical exam.
Imaging is used to assess the hernia and create a personalized plan.
Robotic repair is performed with mesh reinforcement through small insicion.
You'll receive guidance for a smooth recovery and return to normal activities.
No. Mesh is frequently used for ventral and incisional hernia repair because it can reinforce the abdominal wall and reduce recurrence, especially for larger defects. However, some small or selected hernias may be repaired without mesh. The decision depends on defect size and location, tissue quality, contamination or infection risk, previous repairs, and the overall reconstruction plan.
Sometimes. A robotic approach may be useful for selected recurrent ventral or incisional hernias because it can provide detailed visualization and help with dissection, suturing, mesh placement, and abdominal wall reconstruction. Prior mesh, scar tissue, hernia size, and the complexity of the previous repair all influence whether a robotic approach is appropriate.
Abdominal wall reconstruction is a more complex hernia operation designed to restore the strength and function of the abdominal wall rather than simply cover a defect. It may involve closing the abdominal muscles and fascia, removing or working around prior mesh, placing new reinforcement, and using advanced techniques to bring the abdominal wall back toward its normal anatomy.
It can. Excess body weight can increase pressure on the abdominal wall and may raise the risk of wound problems and hernia recurrence. For selected patients, weight management, smoking cessation, diabetes control, nutrition, and treatment of other modifiable risk factors may be recommended before repair to improve safety and durability.
Restrictions vary widely depending on the size of the hernia and the type of reconstruction performed. Walking is usually encouraged early, but heavier lifting and strenuous abdominal activity may be restricted for several weeks, particularly after complex abdominal wall reconstruction. The surgeon should provide individualized instructions based on the operation and recovery.

The presence of a condition does not automatically mean that surgery is necessary or that a robotic approach is best. Treatment should be based on symptoms, diagnostic findings, anatomy, prior operations, overall health, and the expected risks and benefits of each option.
This page is for general educational purposes and does not replace individualized medical advice. The appropriate treatment and surgical approach depend on the patient’s diagnosis, anatomy, medical history, prior operations, and other clinical factors. A physician-patient relationship is established only after an appropriate clinical evaluation and acceptance into care.